

Going Micro in Leptospirosis Kidney Disease
May 09, 2024
Abstract: Leptospirosis is a zoonotic and waterborne disease worldwide. It is a neglected infectious disease caused by Leptospira spp., as well as a reemerging disease and global public health problem concerning morbidity and mortality both in humans and animals. Leptospirosis emerges as a leading cause of acute febrile illness along with hepatorenal injury in many countries, including Thailand. While most affected persons are symptomatic in acute disease, which is always difficult to differentiate from other tropical diseases, there is growing evidence of subtle manifestations that cause unrecognized chronic symptoms. The kidney is one of the common organs affected by Leptospires. Although acute kidney injury in the spectrum of interstitial nephritis is a well-described characteristic of severe leptospirosis, chronic kidney disease from leptospirosis is widely discussed. Early recognition of severe leptospirosis leads to reduced morbidity and mortality. Thus, in this review, we highlight the spectrum of characteristics involved in leptospirosis kidney disease and the use of serologic and molecular methods, as well as the treatments of severe leptospirosis.
Keywords: acute kidney injury; immune response; interstitial nephritis; leptospirosis

HOW LONG DOES IT TAKE FOR CISTANCHE TO WORK FOR KIDNEY DISEASE PATIENTS?
1. Introduction
Leptospirosis is a zoonotic disease in tropical and subtropical regions. The spread of leptospirosis infection predominantly occurs in the epidemic area during the rainy seasons and flooding. Leptospirosis remains a huge global public health problem with increasing prevalence due to global warming and climate change. Outdoor activities, such as rafting, canoeing, triathlons, or bathing in natural bodies of water, have been reported as risk factors for leptospirosis infection [1,2], while occupational risks are associated with some careers, including farm work, veterinary medicine, military, fieldwork research, and living near a rubber tree plantation [2,3]. The disease transmission of leptospirosis mostly occurs from direct contact (especially with the non-intact skin barrier of the host) with contagious secretions (urine) from the infected or carrier animals as well as environmental contaminants, such as water and soil, where pathogenic Leptospira can survive for several weeks [2]. Several wild animals have been reported as reservoir hosts, but the brown rat (Rattus norvegicus) is the most important reservoir reported in many regions worldwide [4]. Despite the inconclusive pathogenesis of leptospirosis, the interplay between host immune responses and the spirochete (Leptospira strain) is recognized as critical for the disease presentation in the acute or chronic phases.

The kidney is the main target of Leptospira in both the acute and chronic phases of infection. The clinical course of severe leptospirosis is biphasic characteristics [1–4]. First, leptospires penetrate the host mucocutaneous barriers leading to an immune phase that causes overwhelming antibody production as well as urinary shedding. Then, in the immune phase, leptospires are eliminated from systemic organs but not kidneys [2]. Hence, the distribution of leptospires in the kidney during the acute phase may affect the deterioration of renal function during the chronic phase. Acute kidney injury (AKI) following leptospirosis is characterized by acute tubulointerstitial nephritis from either immune response against microbial molecules or other factors (such as hyperbilirubinemiamia or rhabdomyolysis-induced myoglobinuria), accompanied by renal tubular microinstruction. The subacute and chronic presentation of leptospires in renal proximal tubules in a carrier state can progress to chronic tubulointerstitial nephritis (CTIN) and fibrosis [5]. Consequently, manipulating host immune responses to the pathogen might prevent chronic kidney disease (CKD) and multi-organ damage from leptospirosis. For this reason, asymptomatic leptospirosis kidney disease should be considered for the differential diagnosis of renal fibrosis and CKD of unknown causes, particularly for patients who live in epidemic areas.
The kidney is the main target of Leptospira in both the acute and chronic phases of infection. The clinical course of severe leptospirosis is biphasic characteristics [1–4]. First, leptospires penetrate the host mucocutaneous barriers leading to an immune phase that causes overwhelming antibody production as well as urinary shedding. Then, in the immune phase, leptospires are eliminated from systemic organs but not kidneys [2]. Hence, the distribution of leptospires in the kidney during the acute phase may affect the deterioration of renal function during the chronic phase. Acute kidney injury (AKI) following leptospirosis is characterized by acute tubulointerstitial nephritis from either immune response against microbial molecules or other factors (such as hyperbilirubinemiamia or rhabdomyolysis-induced myoglobinuria), accompanied by renal tubular microobstruction. The subacute and chronic presentation of leptospires in renal proximal tubules in a carrier state can progress to chronic tubulointerstitial nephritis (CTIN) and fibrosis [5]. Consequently, the manipulation of host immune responses to the pathogen might prevent chronic kidney disease (CKD) and multi-organ damage from leptospirosis. For this reason, asymptomatic leptospirosis kidney disease should be considered for the differential diagnosis of renal fibrosis and CKD of unknown causes, particularly for patients who live in epidemic areas.
The diagnosis of leptospirosis is also a key step toward a better outcome. Although several rapid and improved diagnostic tests for leptospirosis are now available [6], negative results should not be considered to exclude leptospirosis, especially in highly suspicious cases. Empirical therapy should be started concurrently with suspicion of a diagnosis of leptospirosis because early antimicrobial therapy administration may prevent patients from progressing to more severe forms of the disease.

2. Epidemiology
Although the actual incidence of leptospirosis worldwide is not precisely known, the age and gender-adjusted disease morbidity models estimated annually 1.03 million cases and 58,900 deaths worldwide [7], where the highest estimated disease morbidity and mortality were observed in South and Southeast Asia, Oceania, Caribbean, Andean, Central, and Tropical Latin America, and East Sub-Saharan Africa [7]. In Thailand, the incidence of leptospirosis is reported at around 6.6 per 100,000 population, with a 1.5% fatality rate. The northeastern region has the highest incidence (12.5 per 100,000 population), depending on the season, and the highest incidence occurs during the rainy season from August to October each year [8]. According to a recent study by Torgerson et al. [9], a total of 2.90 million Disability Adjusted Life Years, estimated >70% of the global cholera burden as the estimation of the 2010 Global Burden of Disease (GBD) reports [10]. As such, leptospirosis seems to be the biggest zoonotic-related health disease burden [7]. Furthermore, with the increasing frequency of flooding due to global warming in both developed and developing countries, leptospirosis is not limited to tropical countries. Another aspect of the problem is a semantic or epistemological issue because over 50% of leptospirosis patients with or without kidney involvement are asymptomatic or exhibit mild symptoms [11]. Thus, it is important to consider the rates of leptospirosis in patients with infections with AKI involvement or those with CKD of uncertain etiology, as leptospirosis could contribute to the unrecognized pathogenesis. The complications of leptospirosis can include multiple organ damage in 5–10% of total infected cases [12]. Moreover, leptospirosis causes AKI, at rates varying from 10–88% depending on the definition of AKI [13,14]. The Kidney Disease Improving Global Outcomes (KDIGO) clinical practice guidelines for AKI in 2012 define AKI as a change of either serum creatinine (SCr) exceeding 0.3 mg/dL within 48 h or an increase in SCr to 1.5 times the baseline value within the previous one week along with decreased urine output (Figure 1). In Teles et al.'s [14] retrospective study of 205 leptospirosis patients with AKI, 55.1% of patients with AKI were classified as KDIGO 3, while 16.1% were classified as KDIGO 1 and 17.6% as KDIGO 2. However, the observed data seem to indicate a high prevalence of AKI as defined by the KDIGO criteria despite the mild expression of leptospirosis. This could be due to oversensitivity of the KDIGO criteria, or a high incidence of AKI in leptospirosis regardless of the degree of severity. Robust validation of the true incidence of AKI in leptospirosis with diverse definitions is needed. The risk factors of leptospirosis vary based on the country and area of study and can be classified as occupational, behavioral, and environmental risk factors. Kamath et al. [15] conducted a population-based case-control study in Southern India in which occupational factors, such as outdoor activities (odds ratio [OR] of 3.95) or the presence of cuts or wounds on body parts during work (OR: 4.88), and environmental factors, such as contact with rodents through food contamination (OR: 4.29) or contact with soil or water contaminated with rat urine (OR: 4.58), were found to be associated with leptospirosis. Meanwhile, a retrospective study from Thailand revealed that living near rubber tree plantations as well as bathing in natural bodies of water two weeks before the illness was significantly associated with an increased risk of severe leptospirosis compared to non-severe leptospirosis (OR: 12.00 and 7.25, respectively). Notably, most patients were exposed while bathing in stagnant water (41.9%), slowly flowing water (29.0%), and mud (29.0%) [2]. Moreover, leptospirosis cases are increasing in terms of travel-related infection. The estimated annual incidence of travel-related leptospirosis in the Southeast Asia region is approximately 1.78 per 100,000 travelers per year compared with an incidence of endemic cases of 0.06 per 100,000 population per year (risk ratio [RR] 29.6), which is predominately related to water-related activities [16].

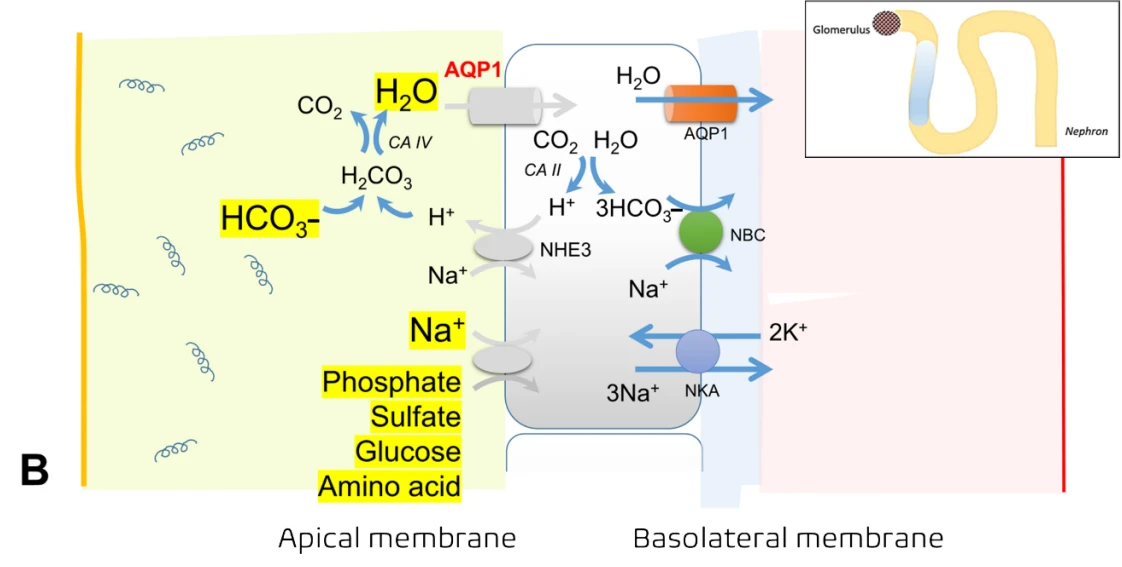
The mechanisms of proximal tubular defects caused by Leptospira spp. (A) Illustration of normal physiology and the important channels involved in the regulation of intraluminal bicarbonate, phosphate, sulfate, glucose, and amino acids via the aquaporin (AQP)-1 channel, sodium– hydrogen exchanger (NHE) 3 (or sodium–hydrogen antiporter 3), and sodium/phosphate cotransporter (Na/Pi). (B) Leptospira causes injury along proximal tubules, leading to altered regulation of these luminal gate channels in both apical and basolateral membranes, for instance, the reduction in NHE3, AQP1 channels, and the decreased expression of α-Na+ /K+ -ATPase along the apical and basolateral membranes, respectively. Hence, in the luminal part, there is an accumulation of free water (causing polyuria), sodium wasting, and characteristics of Fanconi's tubular dysfunction, inincluding bicarbonaturia, hyperphosphaturia, and glucose

3. Pathophysiology
3.1. Acute Kidney Injury in Leptospirosis
AKI is a common manifestation of leptospirosis. Renal involvement in leptospirosis varies from asymptomatic urinary abnormalities to severe AKI that requires supportive dialysis. The most common renal pathology in leptospirosis is acute tubulointerstitial nephritis (ATIN), whereas hypokalemia and sodium wasting are common laboratory findings. Interestingly, AKI caused by leptospirosis is usually non-oliguric, and hypokalemia accounts for 45–50% of all AKI cases [17]. ATIN from leptospirosis is characterized by diffuse interstitial edema and mononuclear cell infiltration. Notably, glomerular involvement in leptospirosis is less common. Leptospirosis-induced vasculitis is rare, with unfavorable renal outcomes that can be attenuated by corticosteroid administration [18–21]. Different mechanisms have been proposed for non-oliguric, hypokalemic AKI in leptospirosis (discussed below).
Tubular Dysfunction and Related Electrolyte Disturbances
Several tubular defects have also been reported, such as bicarbonaturia, glucosuria decreased proximal tubule sodium reabsorption, and high excretion of phosphate and uric acid, also known as Fanconi syndrome [11,22,23]. Reductions in sodium–hydrogen ex-changer isoform 3 (NHE3), which is expressed along with aquaporin 1 (AQP1) in the apical membrane of the proximal tubule, and a decrease in α-Na+/K+–ATPase [24] cause several complications. Hyponatremia in leptospirosis is attributed to several causes, including increased urinary sodium loss, cellular efflux of sodium from Na+/K+–ATPase defects, increased levels of antidiuretic hormone (ADH), and resetting of the osmoreceptors [25]. Accordingly, the combination of the clinical clues of hyponatremia, hypokalemia, and non-oliguric AKI (or polyuria) are unique characteristics of leptospirosis nephropathy.
In addition, downregulation of the sodium-potassium-2-chloride co-transporter (NKCC2) in the medullary thick ascending limb (mTAL) of the loop of Henle may also explain the loss of sodium and potassium in the urine [24,26,27] (Figure 2). Polyuria or non-oliguric AKI occurring during the first stage of leptospirosis might be another symptom related to the reduced expression of aquaporin 2 (AQP2) and a urinary concentration defect due to resistance of the inner medullary collecting duct to vasopressin. During the recovery phase of AKI, AQP2 expression increases as a compensatory mechanism [24].
Hypomagnesemia is also common in leptospirosis patients with AKI from magnesium wasting [28]. One experimental study also reported renal magnesium wasting secondary to decreased NKCC2 on the apical membrane of mTAL [27] (Figure 2). Accordingly, hypomagnesemia and hypophosphatemia caused by hypermagnesuria and hyperphosphaturia, respectively, should be closely monitored during leptospirosis infection. Hyhypomagnesemia from tubular dysfunction in leptospirosis may cause dramatic changes in magnesium homeostasis, which needs substantial amounts of magnesium replacement, especially in patients with myalgia, lethargy, and arrhythmias. On the other hand, rapid correction of hypomagnesemia may unintentionally increase circulating magnesium levels because leptospirosis may contribute to AKI, which may decrease magnesium clearance. Likewise, severe hypophosphatemia (defined as serum phosphate <1.5 mg/dL) from proximal tubulopathy may contribute to metabolic encephalopathy and myopathy. Accordingly, as per the authors' experience, serum magnesium and phosphate levels should be evaluated every 3–5 days and 1–2 days, respectively, particularly in severe leptospirosis.
Interestingly, leptospirosis-related AKI occasionally requires supportive renal replacement therapy in the acute phase of infection. The kidneys may fully recover after the complete course of early antimicrobial therapy. Effective treatment of leptospirosis re-versed tubular dysfunction in an in vitro study [27]. Leptospirosis patients also have more favorable outcomes with non-oliguric than with oliguric AKI [17].

Figure 2. Illustration of the pathogenesis of hypokalemia, hypomagnesemia, and hypocalcemia in leptospirosis kidney disease. (A) Sodium-potassium-2 chloride cotransporter (kidney-specific cation Cl- coupled cotransporter, NKCC2) is an important cotransporter that maintains the homeostasis of intraluminal cations and anions. (B) NKCC2 functions with potassium channels (ROMK) and Paracelliar selective protein channels of magnesium (main) and calcium (minor), called claudin 16 and 19, to maintain intraluminal positive electric charge. (C) Similar to pharmacological inhibition of NKCC2 by furosemide, loss of NKCC2 controlling due to tubular injury caused by Leptospira, leads to loss of intraluminal positive electric charge, which causes decreased reabsorption of magnesium and calcium. Thus, low levels of both magnesium (hypomagnesemia) and calcium (hypocalcemia) in circulation, in turn, provide positive feedback (green arrow) and enhance potassium excretion into the lumen to maintain homeostasis. The Ca/Mg receptor is located at the basolateral membrane so far called the calcium sensing receptor (CaSR), which is the key molecular player involved in sodium, potassium, and chloride transport by the thick ascending limb. During hypocalcemia and/ or hypomagnesemia, inactivation of basolateral CaSR enhances ROMK. Eventually, a large amount of potassium will be lost in urine
3.2. Leptospirosis with Systemic Inflammatory Response Syndrome (SIRS)
Severe leptospirosis is complicated by sepsis and septic shock [29,30]. In the early phase, leptospirosis is related to an overwhelming activation of inflammasomes and proinflammatory cytokines, causing kidney inflammation and subsequent damage. Leptospira can be found in the proximal tubular cells at day 10 of the infection, and it can subsequently be found in the tubular lumen at day 14 of the infection [31]. Its antigens are also found in the proximal tubular cells, macrophages, and the interstitium [32].
The outer membrane proteins (OMPs) of Leptospira contain antigenic and virulent compounds, including lipoproteins, lipopolysaccharides (LPS), and peptidoglycans, which determine the host responses. In animal models of sepsis, LPS or endotoxin cause detrimental effects on the host [33,34]. Leptospira LPS, located on the OMP, appears to be the major antigen that affect immunity to Leptospira, and believe its functions are relevant to host-pathogen interactions which determine virulence and pathogenesis. To elucidate the mechanisms of tubule-interstitial injury caused by Leptospira, the Leptospiral OMPs were extracted from cultured mouse renal epithelial cells, which showed the expression of a variety of genes related to tubular cell injury and inflammation [35]. The Leptospiral OMPs activate nuclear transcription factor kappa B (NF-KB), activator protein-1, and several downstream genes expressed in the medullary thick ascending limb cells [35]. LipL32, a major pathogenic lipoprotein on the OMP, induces tubulointerstitial nephritis-mediated gene expression in mouse proximal tubular cells and is a prominent immunogen during leptospirosis infection in humans [36]. In addition, LipL32 is a hemolysin that causes hemolysis of erythrocytes during Leptospira infection [37], and it directly affects proximal tubular cells by substantially increasing the gene and protein expression of several pro-inflammatory cytokines, including inducible nitric oxide (iNOS), monocyte chemoattractant protein-1 (MCP-1), and tumor necrosis factor-α (TNF-α). Therefore, the identification of novel OMPs of the Leptospira should remain a primary focus for increasing knowledge of leptospirosis pathogenesis and treatment.
Toll-like receptors (TLRs) are proteins that recognize specific molecular patterns of pathogens and represent the first line of immune defense mechanisms in the innate immune response. The effects of TLRs were evaluated to determine whether TLRs could mediate the inflammatory response induced by Leptospiral OMP in renal proximal tubular cells. Interestingly, only TLR2 but not TLR4 increased the expression of iNOS and MCP-1. Accordingly, the findings indicate that the stimulation of iNOS and MCP-1 caused by pathogenic Leptospiral OMPs, in particular LipL32, in proximal tubular cells requires TLR2 (usually co-expressed with TLR1) for the early inflammatory response [5].
Then, a cascade of inflammation is activated in the renal tubular cells, as leptospirosis induces interleukin (IL)-1β and IL-18 secretion from human macrophage cells through reactive oxygen species and cathepsin B mediated-NLRP3 inflammasome activation [38]. Other circulatory cytokines and chemokines, including IL-6, IL-10, monocyte chemoattractant protein-1 (MCP-1), and TNF-α [39], are also produced during leptospirosis infection. Acute cytokine and chemokine surges occurring in leptospirosis patients can cause a detrimental syndrome of sepsis and severe sepsis due to an imbalance between pro- and anti-inflammatory responses. Increased levels of MCP-1, IL-11, and small inducible cytokine A2 occur during leptospirosis with thrombocytopenia [40]. These findings infer the role of cytokine and chemokine production during the acute and subacute phases of leptospirosis infection. Conversely, chronic inflammasome activation may be the pathway that leads to renal parenchyma fibrosis or CKD [41].
AKI following leptospirosis may thus arise due to acute tubular necrosis (ATN) from ischemia and poor renal tissue perfusion as the result of sepsis and septic shock. In addition, sepsis-associated AKI (sepsis-AKI) in leptospirosis is also possible, especially in patients with a low blood pressure episode. Evidence from both experimental and clinical studies shows that septic shock develops into a sepsis-related immunosuppression state, leading to the death of the host because of innate and adaptive immunity disturbances [42]. Therefore, circulating cytokines and chemokines may interfere with the immune response in severe leptospirosis; for example, low circulating neutrophil levels may be associated with impaired antimicrobial activity [43–45].

3.3. Chronic Kidney Disease in Leptospirosis
The consequences of ATIN caused by leptospirosis infection include tubular atrophy and interstitial nephritis in the event of unsuccessful treatment or incomplete recovery. In an attempt to elucidate the causal association between Leptospira and renal fibrosis, the effects of OMP from pathogenic Leptospira on the production and accumulation of extracellular matrix have been explored [46]. The binding of Leptospiral OMP to proximal tubular cells, HK-2 cells, led to an increase of type I and type IV collagens in a dose-dependent manner. Likewise, the active transforming growth factor (TGF)-β1 secretion was increased twice following the addition of Leptospira OMP, while anti-TGF-β1-neutralizing antibodies attenuated the increased production of type I and type IV collagen, indicating the participation of TGF-β1 in the cascade. This phenomenon was confirmed by the increased nuclear translocation of SMAD3 after the administration of Leptospiral OMP, and overexpression of the dominant-negative SMAD3 prevented the Leptospiral OMP-induced increase of type I and IV collagen production without any effects on metalloproteinase activity [46]. This demonstrated the effects of Leptospiral OMP in terms of enhancing extracellular matrix synthesis mediated by the TGF-β1/SMAD pathway.
Although data from both in vitro and in vivo studies indicate the possibility of CKD and renal fibrosis due to leptospirosis infection [46–48], the results from both a meta-analysis [49] and a long-term, three-year follow-up study is inconsistent, as no lepleptospirosis patients with dialysis dependence were reported [50]. Chronic tubulointerstitial nephritis (CTIN) is a common lesion associated with long-standing leptospirosis that may lead to CKD of unknown etiology and subsequent renal failure. Sustained tubulointerstitial lymphocyte infiltration might be a key factor resulting in the progression to CKD [50]. Perhaps, TLRs may be involved in the AKI–CKD continuum in leptospirosis because TLRs are known to be a key factor in the primary response to both innate and adaptive immunity [47] as well as ischemia-reperfusion injury, glomerulonephritis, and sepsis-AKI. Therefore, further studies should seek to identify the molecular factors that may act as a danger signal by triggering the inflammatory response to different exogenous and endogenous noxious stimuli.




