

Microglial Adenosine Receptors: From Preconditioning To Modulating The M1/M2 Balance in Activated Cells Part 2
Mar 01, 2024
3. Potential of Adenosine Receptors (AR) as Therapeutic Targets
After several inconveniences in the race to obtain new drugs that act on ARs, there is evidence of excellent prospects for the approval of the human use of ligands of these receptors. For many years, adenosine itself was the only drug targeting ARs that was approved for human use.
In recent years, with the continuous advancement and application of technology, more and more studies have shown a close connection between AR technology and memory. Through the interaction between the virtual and real world, AR technology can stimulate people's senses, provide intuitive and vivid information, and enhance people's knowledge and understanding. At the same time, AR technology can provide personalized learning and training experiences, bringing new opportunities to people's intellectual and educational development.
Many studies and practices have confirmed the connection between AR technology and memory. For example, in medicine and psychology, researchers have used AR technology to develop many intervention programs for memory impairment and cognitive impairment. These solutions are based on the theories of modern neuroscience and cognitive psychology, combined with the advantages of AR technology, to improve people's memory and learning abilities through a variety of methods and means, such as virtual training, simulated real environments, enhanced representations, etc.
In addition, AR technology can also be applied in the field of education and training to provide students and professionals with a comprehensive and personalized learning experience. Using AR technology, students can interact with objects or scenes in a virtual environment, mapping the knowledge they have learned into specific scenes, and gaining a deeper understanding and memory. In terms of vocational training, AR technology can provide professionals with a more intuitive and practical training experience, helping them master and apply the required skills and knowledge faster.
To sum up, the relationship between AR technology and memory has broad application prospects and potential. AR technology provides people with a better learning and training experience and brings more fun and innovative thinking. I believe that in the future development, AR technology will continue to expand and improve, bringing more benefits and results to people's education, health, and lives. It can be seen that we need to improve memory, and Cistanche deserticola can significantly improve memory, because Cistanche deserticola has antioxidant, anti-inflammatory, and anti-aging effects, which can help reduce oxidation and inflammatory reactions in the brain, thereby protecting the health of the nervous system. In addition, Cistanche deserticola can also promote the growth and repair of nerve cells, thus enhancing the connectivity and function of neural networks. These effects can help improve memory, learning, and thinking speed, and may also prevent the development of cognitive dysfunction and neurodegenerative diseases.

Click Know to improve short-term memory
Despite the early discovery of the actions of adenosine in the cardiovascular system [78], to our knowledge, there are no AR-related drugs in the line to combat cardiovascular disease.
However, adenosine has saved lives in the emergency room as it converts paroxysmal tachycardia into sinus rhythm. The main basis for proposing this intervention, only performed at hospitals, was the work performed in the second half of the fifties by different laboratories. The data from Berne's laboratory allowed patenting the use of the nucleoside for combating tachycardia [79–81].
It is intriguing why there are no new drugs targeting adenosine receptors able to combat heart diseases, especially after the finding that adenosine A2A receptor (A2AR) antagonists, which are safe, are efficacious in reverting abnormal calcium handling in cells from patients with atrial fibrillation [82–84], a disease lacking efficacious medication. In general, AR antagonists are safe.
The most consumed (worldwide) psychoactive compounds are AR antagonists. We refer to natural methylxanthines, e.g., caffeine in coffee, theophylline in tea, and theobromine in cocoa. Those methylxanthines are considered as generally safe [76,85–87]. They have been approved for human use; they are present in a variety of OTC (over-the-counter) medications and some therapies for respiratory diseases.
In addition, consumption of methylxanthines decreases the risk of suffering from neurodegenerative diseases, whose main risk factor is age [67,71,72,76,86,88,89]. A2AR antagonists have been developed in parallel in different pharmaceutical companies.
They were designed to enter the brain and be effective for Parkinson's disease (PD), a neurodegenerative disease that involves the degeneration of dopamine-producing neurons in the substantia nigra. Due to the opposite dopamine-adenosine functionality in the striatum, it was hypothesized that the action of dopamine in PD patients could be enhanced if the A2AR was blocked [90–96].
Furthermore, experiments in animal models suggested that blockade of the A2AR affords neuroprotection, thus raising the possibility that AR antagonists delay the progression of this neurodegenerative disease [74,75,97–107].
Highly selective A2AR antagonists were developed and a few years ago the first-in-class drug was approved for coadjuvant therapy in PD. It was KW-6002, also known as istradefylline (PD) [108,109] that was first approved in Japan (NouriastTM) and years later, in the USA (NourianzTM).
Such decisions by regulatory bodies in two different and populated countries pave the way for the approval of AR ligands for a variety of diseases. Even in cancer, there is great hope because AR antagonists improve the efficacy of immunotherapies [110–114].

4. Neuron vs. Glia in Neurodegeneration
A fundamental question to address in the field of neuroprotection is whether to target neurons or glia. In our opinion, neurons have been at the center of the stage to explore and test neuroprotective interventions to slow the progression of neurodegenerative diseases. However, direct action on neurons is challenged by the poor survival prospects of neurons that are having problems and will, sooner or later, die.
Blocking a presumed death mechanism in neurons may not be effective for senescent or dysfunctional neurons [115]. Cell therapy may overcome such problems as neuroprotection consisting of increasing the number of cells without necessarily affecting the fate of existing neurons.
On the contrary, it is doubtful that gene therapy with viral vectors, aimed at infecting suffering neurons, can prevent neurodegeneration: it may help reduce symptoms, but there is no reason to believe that gene therapy can increase the lifespan of an infected neuron. Neurons require glia to survive and maintain proper functionality. Glial cells can certainly help accelerate cell death, but they are effective in preventing or delaying neuronal death [115].
It is well known that astroglia exchange regulatory molecules with neurons which also provide molecules necessary for energy production. Neuron-microglia interaction is less evident under homeostatic conditions. However, these interactions play an important role in cerebral hypoxia/ischemia and neurological diseases associated with inflammation.
In addition, the functionality of the microglia is essential in physiological
neuronal death, which occurs both in the development of the nervous system and later
in human life. Neuron-microglia interactions have two sides, one related to the removal
of neuronal components after death and the other aimed at both starting and stopping
inflammation.
In summary, the glia seem a better target than neurons to provide neuroprotection. In keeping with the title of the special issue in which this article is included, we
will address the potential of microglia to protect neurons and/or provide neuroprotection
through proper manipulation of the M1/M2 phenotypic balance (see below).
5. Microglia
Microglia are considered part of the immune system located in the CNS. Their role is similar to that of blood macrophages, which are characterized by two functions, phagocytic and inflammatory. Microglial cells were identified by Pio del Rio Hortega, a contemporary of Santiago Ramón y Cajal [116–118]. Activation of microglia was, for several years, considered detrimental; activated cells were described as reactive microglia (see [119] for review).
It is now known that these cells are important for neuroprotection and the reason is that there are different phenotypes resulting from microglial activation [11]. Macrophages are key in the fight against a variety of infections of parasitic, fungal, bacterial, and viral origin.
From a resting state, they undergo activation to display a M1, or proinflammatory phenotype, or follow an alternative activation route leading to the so-called M2 phenotype, which participates in the resolution of inflammation and cleanup.
The properties of the two populations in the context of bacterial infection were concisely described in [120]: "Based on limited numbers of markers, activated macrophages can be classified as classically activated (M1) macrophages that support microbicidal activity or activated (M2) macrophages that are not competent to eliminate pathogens".
Ontogenesis and anatomical studies led to i) recognizing microglia as resident cells in the CNS, ii) recognizing that these resident cells may activate, and iii) major lesions may lead to the entrance and activation of macrophages from blood [121,122]. Under homeostatic conditions, the microglia are at rest (M0). Any damaging condition results in cell activation that, analogously to macrophages, may lead to different microglial phenotypes. As reviewed elsewhere, the main activation phenotypes are M1 and M2, although the M2, depending on the specific function and the markers that are expressed, may be subdivided into 2a, 2b, 2c, and 2d [18]. GPCRs are involved in the regulation of microglial polarization.
Important clues related to microglial polarization come from detailed studies on how neuropeptides inhibit classical microglial activation thus suggesting that they may induce M2 polarization. The actions of the vasoactive intestinal peptide (VIP) on reducing microglial production of pro-inflammatory cytokines are due to activation of vasoactive intestinal peptide receptors 1 and 2 (VPAC1 and VPAC2) [123,124]. Neuroprotection by VIP acting on microglial receptors may be due to IL-4 production and protection of hippocampal neural stem/progenitor cells [125].
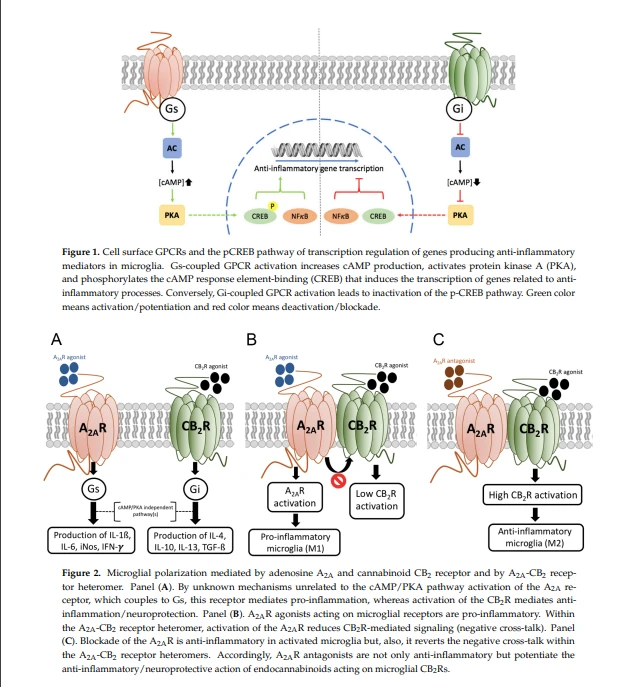
Pathways engaged upon GPCR activation can regulate microglial activation and polarization. Gs coupling and PKA pathway activation impact NFKB transcriptional activity thus inhibiting chemokine gene expression. Expression of complexes formed by CREB binding protein (CBP) and NFKB may be regulated via GPCRs (Delgado, 2002). Accordingly, GPCRs via Gs/Gi, i.e., via modification of cAMP levels, modulate microglial activation by balancing the action of these transcription factors (Figure 1) [126,127].
Neuropeptides acting via Gs/cAMP/PKA inhibit MAPK4, impact the JNK pathway, and the composition of cJun/cFos and cJunB complexes, thus reducing the expression of IFN-gamma, CD40, CXCL10, and iNOS [126,128]. However, not all Gs-coupled receptors in microglia mediate neuroprotection, adenosine A2A receptor activation increases the expression of nitric oxide in microglia [129] while cannabinoid receptors mediate neuroprotection despite they are coupled to Gi.

This means that different pathways impact the final output in terms of the production of pro-inflammatory or anti-inflammatory mediators (Figure 2A). It would be very interesting to study the time course variations in the activation program of different pathways. Consistent with differences in protein expression/functionality in microglia throughout inflammation, there are GPCRs expressed at low levels in resting microglia but overexpressed upon activation.
A2A receptors are one example, they are barely expressed in resting microglia but are markedly upregulated in surrounding microglial plaques found in AD patients [130]. Interestingly, the adenosine A1 receptor is also up-regulated in neurodegenerative structures in AD and its activation modulates both phosphorylation and translocation of tau and processing of the amyloid precursor protein [130].
There is a kind of controversy surrounding the term "neuroinflammation" because it is doubtful that CNS becomes inflamed. Moreover, the function of activated microglia in CNS development is not considered to result in neuroinflammation.
Therefore, it is suggested that neuroinflammation should be substituted by microglial activation or CNSpseudoinflammation 6]. Microglia become activated in physiological/healthy CNS development. If neuronal death occurs (i) occasionally throughout human life and (ii) progressively in healthy-aged individuals, microglia are likely to be activated.
In various pathological conditions, including neurodegenerative diseases, the microglia are activated. When should microglial activation be considered inflammation? What if some type of microglial activation is needed for neuronal survival in both health and disease? Moreover, neuronal death requires the removal of that debris by the phagocytic activity of activated microglia.
Undoubtedly, the overproduction of pro-inflammatory cytokines when there is an imbalance in the M1/M2 ratio can lead to further neuronal death. In summary, microglial activation is a physiological mechanism that can become dangerous and potentiate certain neuropathology if the skewing towards the M2 phenotype does not occur in the appropriate period.
Although the expression of ARs depends on the state of the microglia (resting or activated) and the specific phenotype, all ARs, except the A2B, have been reported to be expressed in resting cells. [131,132]. Expression may vary depending on microglial location in the brain. The A2B receptor is likely expressed in M1 and/or M2 skewed cells.
The A2BR is present in primary microglia from rat forebrain and its activation (in resting cells) engages the p38 MAPK pathway to induce interleukin(IL)-6 release [133]. After an excitotoxic insult in the cortex or striatum, A2AR antagonists differentially modulate astrogliosis and microglia activation. In microglia activated upon quisqualic acid-induced excitotoxicity, A2AR antagonists inhibit the expression of cyclooxygenase-2 (COX-2) [134].
On the other hand, excitotoxicity by glutamate activates glutamate NMethyl-D-Aspartate (NMDA) receptors expressed in microglia and leads to the release of pro-inflammatory cytokines [135]. A vicious circle sustaining M1 microglia and neuronal cell death may be established unless any physiological action is restored to homeostasis or any pharmacological intervention.

For instance, targeting adenosine receptors leads to M2 skewing. NMDA receptor function in microglia is increased by direct interactions with A2ARs, increasing the possibility that A2AR antagonists may be neuroprotective by reducing the excitotoxic load associated with neurodegenerative diseases [136].
For more information:1950477648nn@Gmail.com





